Employee Benefit Options
Medical Benefits
Overview
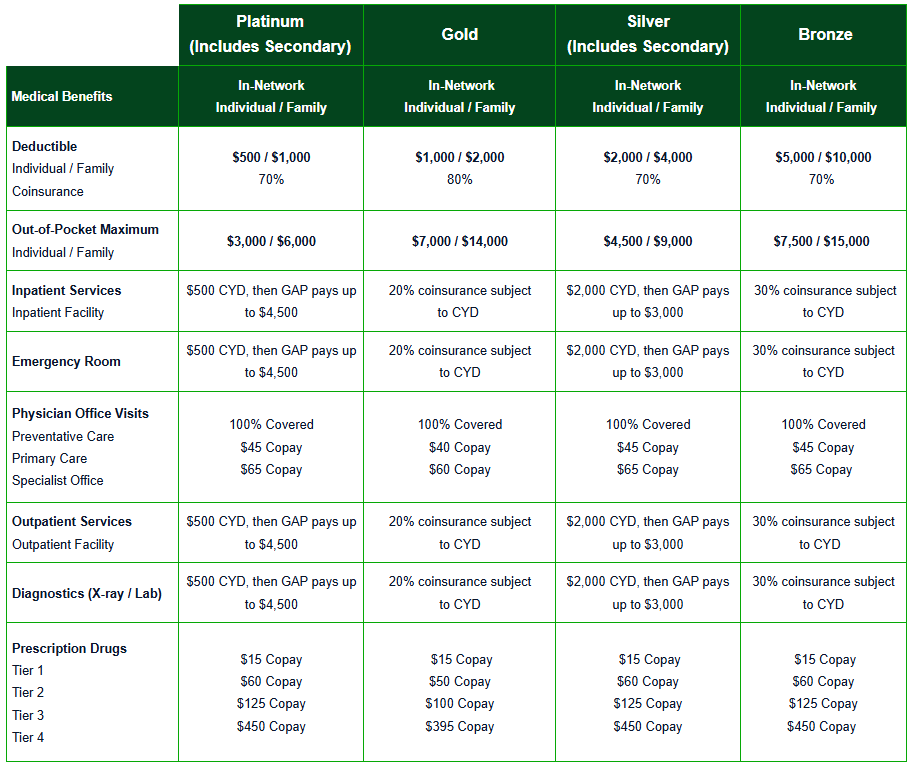
You have four medical plan options: the Platinum Plan, Gold Plan, Silver Plan and the Bronze Plan. All plans are administered by BlueCross BlueShield (BCBS) and provide the maximum benefits when a BCBS provider is used for services.
The ALVMA Platinum Plan and Silver Plan includes both primary and secondary insurance. The secondary plan does not cover office visits or prescription drug copays or home health services.
NOTE: The out-of-pocket maximum excludes office visits and prescription drug co-pays.
For rate inquiries, please contact Patrick Pittman at 205-215-8152 or via email at patrick@southviewbenefits.com
| Platinum (Includes Secondary) |
Gold | Silver (Includes Secondary) |
Bronze | |
|---|---|---|---|---|
| Medical Benefits | In-Network Individual / Family |
In-Network Individual / Family |
| Deductible Individual / Family Coinsurance |
$500 / $1,000 70% |
$1,000 / $2,000 80% |
$2,000 / $4,000 70% |
$5,000 / $10,000 70% |
| Out-of-Pocket Maximum Individual / Family |
$3,000 / $6,000 | $7,000 / $14,000 | $4,500 / $9,000 | $7,500 / $15,000 |
| Inpatient Services Inpatient Facility |
$500 CYD, then GAP pays up to $4,500 |
20% coinsurance subject to CYD |
$2,000 CYD, then GAP pays up to $3,000 | 30% coinsurance subject to CYD |
| Emergency Room | $500 CYD, then GAP pays up to $4,500 | 20% coinsurance subject to CYD |
$2,000 CYD, then GAP pays up to $3,000 |
30% coinsurance subject to CYD |
| Physician Office Visits Preventative Care Primary Care Specialist Office |
100% Covered $45 Copay $65 Copay |
100% Covered $40 Copay $60 Copay |
100% Covered $45 Copay $65 Copay |
| Outpatient Services Outpatient Facility |
$500 CYD, then GAP pays up to $4,500 | 20% coinsurance subject to CYD |
$2,000 CYD, then GAP pays up to $3,000 | 30% coinsurance subject to CYD |
| Diagnostics (X-ray / Lab) | $500 CYD, then GAP pays up to $4,500 | 20% coinsurance subject to CYD |
$2,000 CYD, then GAP pays up to $3,000 | 30% coinsurance subject to CYD |
| Prescription Drugs Tier 1 Tier 2 Tier 3 Tier 4 |
$15 Copay $60 Copay $125 Copay $450 Copay |
$15 Copay $50 Copay $100 Copay $395 Copay |
$15 Copay $60 Copay $125 Copay $450 Copay |
Dental Benefits
Overview
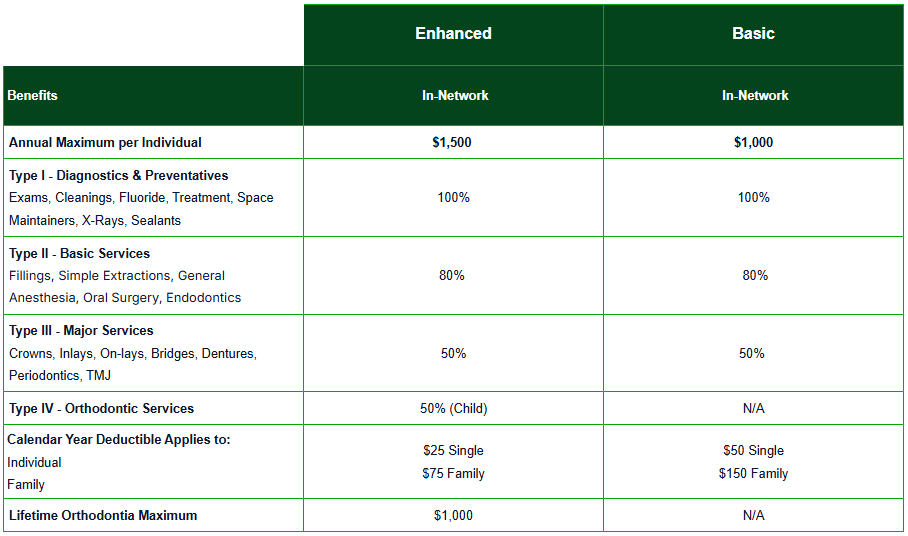
ALVMA offers dental coverage to you through Principal Dental. Your dental plan provides coverage to help with the cost of many dental services including routine cleanings, x-rays, restorative and prosthetic services. The plan includes an extensive network of dental providers. Maximize your benefits by selecting an in-network dentist to save more on all covered services and avoid balance billing.
For rate inquiries, please contact Patrick Pittman at 205-215-8152 or via email at patrick@southviewbenefits.com
| Enhanced | Basic | |
|---|---|---|
| Benefits | In-Network | In-Network |
| Annual Maximum per Individual |
$1,500 | $1,000 |
| Type I - Diagnostics & Preventatives Exams, Cleanings, Fluoride, Treatment, Space Maintainers, X-Rays, Sealants |
100% | 100% |
| Type II - Basic Services Fillings, Simple Extractions, General Anesthesia, Oral Surgery, Endodontics |
80% | 80% |
| Type III - Major Services Crowns, Inlays, On-lays, Bridges, Dentures, Periodontics, TMJ |
50% | 50% |
| Type IV - Orthodontic Services | 50% (Child) | N/A |
| Calendar Year Deductible Applies to: Individual Family |
$25 Single $75 Family |
$50 Single $150 Family |
| Lifetime Orthodontia Maximum | $1,000 | N/A |
Vision Benefits
Overview
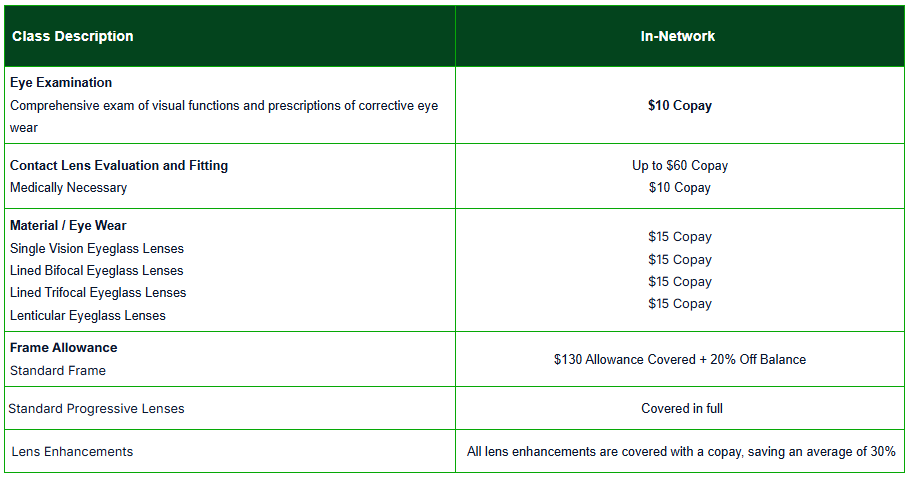
ALVMA offers vision coverage to you through Principal (VSP). Receive the maximum benefits and pay less out-of-pocket by visiting an in-network provider. The network includes provider access points nationwide. A comprehensive vision exam is available every 12 months and you may purchase eyewear in the form of an eyeglass frame and lenses, or contact lenses.
For rate inquiries, please contact Patrick Pittman at 205-215-8152 or via email at patrick@southviewbenefits.com
| Class Description | In-Network |
|---|---|
| Eye Examination Comprehensive exam of visual functions and prescriptions of corrective eye wear |
$10 Copay |
| Contact Lens Evaluation and Fitting Medically Necessary |
Up to $60 Copay $10 Copay |
| Material / Eye Wear Single Vision Eyeglass Lenses Lined Bifocal Eyeglass Lenses Lined Trifocal Eyeglass Lenses Lenticular Eyeglass Lenses |
$15 Copay $15 Copay $15 Copay $15 Copay |
| Frame Allowance Standard Frame |
$130 Allowance Covered + 20% Off Balance |
| Standard Progressive Lenses | Covered in full |
| Lens Enhancements | All lens enhancements are covered with a copay, saving an average of 30% |
Medical Benefits
Overview
You have four medical plan options: the Platinum Plan, Gold Plan, Silver Plan and the Bronze Plan. All plans are administered by BlueCross BlueShield (BCBS) and provide the maximum benefits when a BCBS provider is used for services.
The ALVMA Platinum Plan and Silver Plan includes both primary and secondary insurance. The secondary plan does not cover office visits or prescription drug copays or home health services.
NOTE: The out-of-pocket maximum excludes office visits and prescription drug co-pays.
For rate inquiries, please contact Patrick Pittman at 205-215-8152 or via email at patrick@southviewbenefits.com

Dental Benefits
Overview
ALVMA offers dental coverage to you through Principal Dental. Your dental plan provides coverage to help with the cost of many dental services including routine cleanings, x-rays, restorative and prosthetic services. The plan includes an extensive network of dental providers. Maximize your benefits by selecting an in-network dentist to save more on all covered services and avoid balance billing.
For rate inquiries, please contact Patrick Pittman at 205-215-8152 or via email at patrick@southviewbenefits.com

Vision Benefits
Overview
ALVMA offers vision coverage to you through Principal (VSP). Receive the maximum benefits and pay less out-of-pocket by visiting an in-network provider. The network includes provider access points nationwide. A comprehensive vision exam is available every 12 months and you may purchase eyewear in the form of an eyeglass frame and lenses, or contact lenses.
For rate inquiries, please contact Patrick Pittman at 205-215-8152 or via email at patrick@southviewbenefits.com

